


I’ve always had high cholesterol. In my 30s and 40s, I tried following doctor’s orders by eating low-fat, keeping my weight down, and exercising, but all my work was for naught. My cholesterol numbers just kept getting higher.
After hopelessly fighting my body chemistry for a decade, I became a skeptic of the entire eating-fat-leads-to-high-cholesterol-leads-to-heart-attack industrial complex. I read books like The Great Cholesterol Con and followed Gary Taubes’s anti-establishment medicine blog. Some of those ideas still hold up — that stress contributes to heart disease and that eating high-cholesterol foods like eggs isn’t as bad for you as people once believed.
But there’s also a tidal wave of evidence (here, here, and here) that people with high LDL-C (the “bad” cholesterol) are more likely to have heart events, and that lowering LDL-C reduces the incidence of heart events.
In hindsight my behavior was a classic case of cognitive dissonance. I was seeking out information that supported a worldview that made me more comfortable with my terrifying lab numbers.
By the time I was 47, my LDL-C had skyrocketed to 237 mg/dL. This is not my total cholesterol (which is a misleading metric). My “good” cholesterol HDL-C was also high, 72 mg/dL then and as high as 109 over the years. High HDL-C is supposed to be protective, so I continued to ignore my unsafe LDL-C.
My Family History Was Already in My Records
On every medical intake form, I dutifully filled out the family history section, reliving it every time: my father had a heart attack at 54, my paternal grandfather had a heart attack at 52, and my maternal grandfather dropped dead of a heart attack at 59. So my family history was definitely in the record.

Familial hypercholesterolemia (FH) is a genetic condition that impairs your body’s ability to clear “bad” cholesterol (LDL-C) from your blood. Genetic testing can confirm it, but it is usually diagnosed clinically, from family history combined with lab results, and managed with cholesterol-lowering medication, usually starting with statins. But no doctor ever mentioned familial hypercholesterolemia to me — I suspect because what we write on those intake forms get skimmed. If only I had a document to hand to my doctors to get them to pay attention to my family health history. I’ll go deeper on that in a minute.
While my doctors did suggest I should go on a statin (after preaching diet and exercise), not one said, “With these labs and your family history of heart disease, you may have a genetic disease called familial hypercholesterolemia. With this diagnosis, diet and exercise simply don’t work. Standard treatment is to prescribe a statin for people with familial hypercholesterolemia to reduce chances of a cardiac event.”
I think my 47-year-old, cognitively dissonant brain might have cracked if a doctor had diagnosed me with a disease. My layman’s thinking was: if you have a disease, you take medicine; if you have a high lab number, you work through it.
Then I Got a Scare
After a decade of stubbornly fighting with my doctors about statins, I made the argument to one: “High cholesterol isn’t a disease; the disease is atherosclerosis. Isn’t there a test I can take to see if my arteries are clogged?” He answered, “Yes there is.”
A Coronary Artery Calcium (CAC) scan calculates the calcium plaque burden in the coronary arteries. A score of zero means you don’t have any calcified plaque clogging your arteries. A score greater than zero means you have a disease: coronary artery disease (CAD).
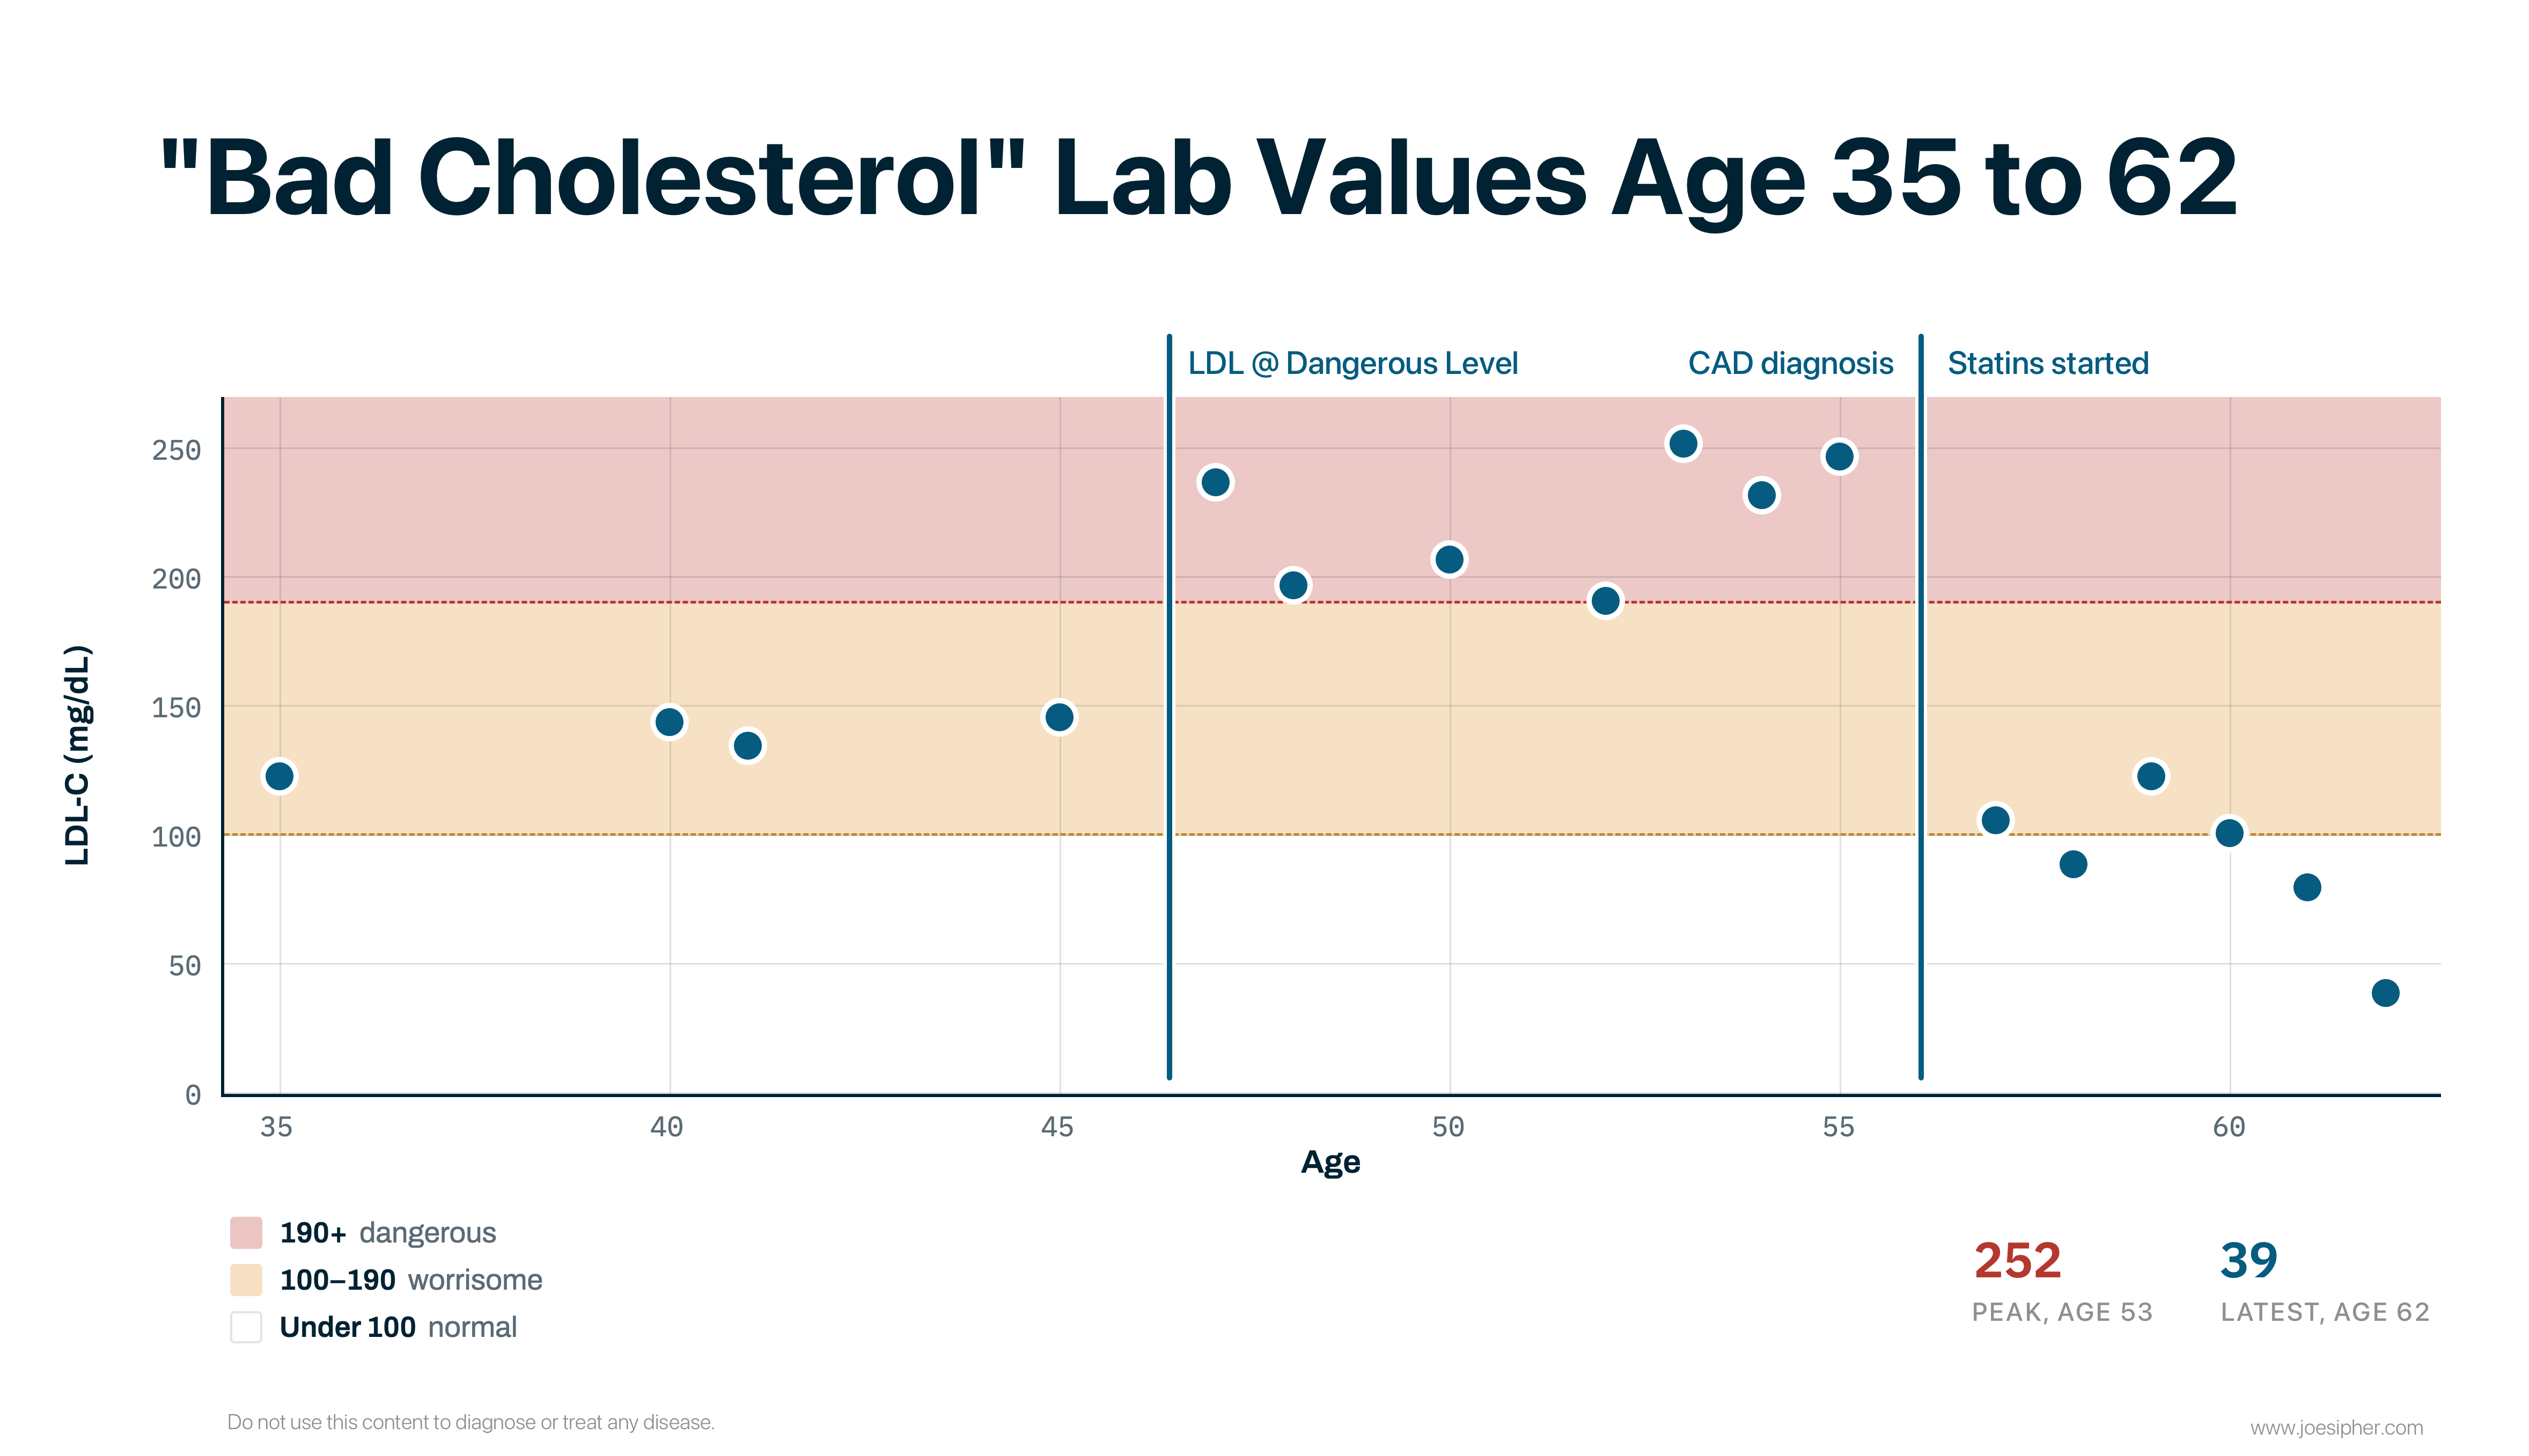
My score was greater than zero, and this shook me enough to start on a statin. As you can see from the chart above, the statin brought my LDL-C down to a safe level and my fears about memory loss and muscle pain side effects did not materialize. I’ve had no side effects, even as my doctors and I agreed to a more aggressive approach.
But I’ll never know the impact of letting my LDL-C ride above 190 mg/dL for a decade.
Why Is Family History Often Ignored?
I had never heard the term familial hypercholesterolemia until I started building HealthScout. It was HealthScout that put the pieces together, telling me to talk to my doctor because my labs and family history were a “classic case” of FH.
At a recent primary care visit, I asked my doctor to add FH to my record. He said, “So you have a family history of heart disease?” To be fair, he was a new doctor and my lab numbers were already in the normal range, but he did have access to records that included my answers on those medical intake forms.
I suspect many doctors deprioritize family history as an input because the data is often so unreliable. Of course it is. The information is often decades old and passed down like a game of telephone. I’ve been working on my own family health history for months now, and I’m still not 100% sure what my paternal grandmother died of or if she had Type 1 or Type 2 diabetes.
But if we can make family health history reliable, it belongs on equal footing with risk factors doctors already act on such as smoking status, exercise, and diet.
My cholesterol story is a microcosm of what happens every day. People’s family health histories of cancer, diabetes, Alzheimer’s, and dozens of other heritable conditions are not taken into account in doctor visits all over the world. And if a doctor doesn’t know a disease runs in your family, they’ll treat you like it doesn’t. You won’t get the early screening for colon cancer or the early mammogram that could save your life, or, in my case, the preventive medicine that could reduce your chances of a serious health event.
HealthScout Family Health History
HealthScout’s new Family Health History feature takes a different approach to the sparse, inaccurate information on those intake forms. Instead of an individual trying to remember all the conditions of generations past, the family works on it collaboratively. Everyone on the bloodline can add or edit information on their own profile and on their blood relatives’ profiles. And it makes sense — maybe you don’t remember how your grandmother died, but your great-aunt lived through it. Even if she’s not on HealthScout, you can ask her and add the info for everyone on the bloodline to share.

Once your family health history has enough valuable information, you can generate a PDF of blood relatives with heritable conditions that you can share with your doctor. If you personally share a document like this, your doctor will more likely pay closer attention to your family health history.
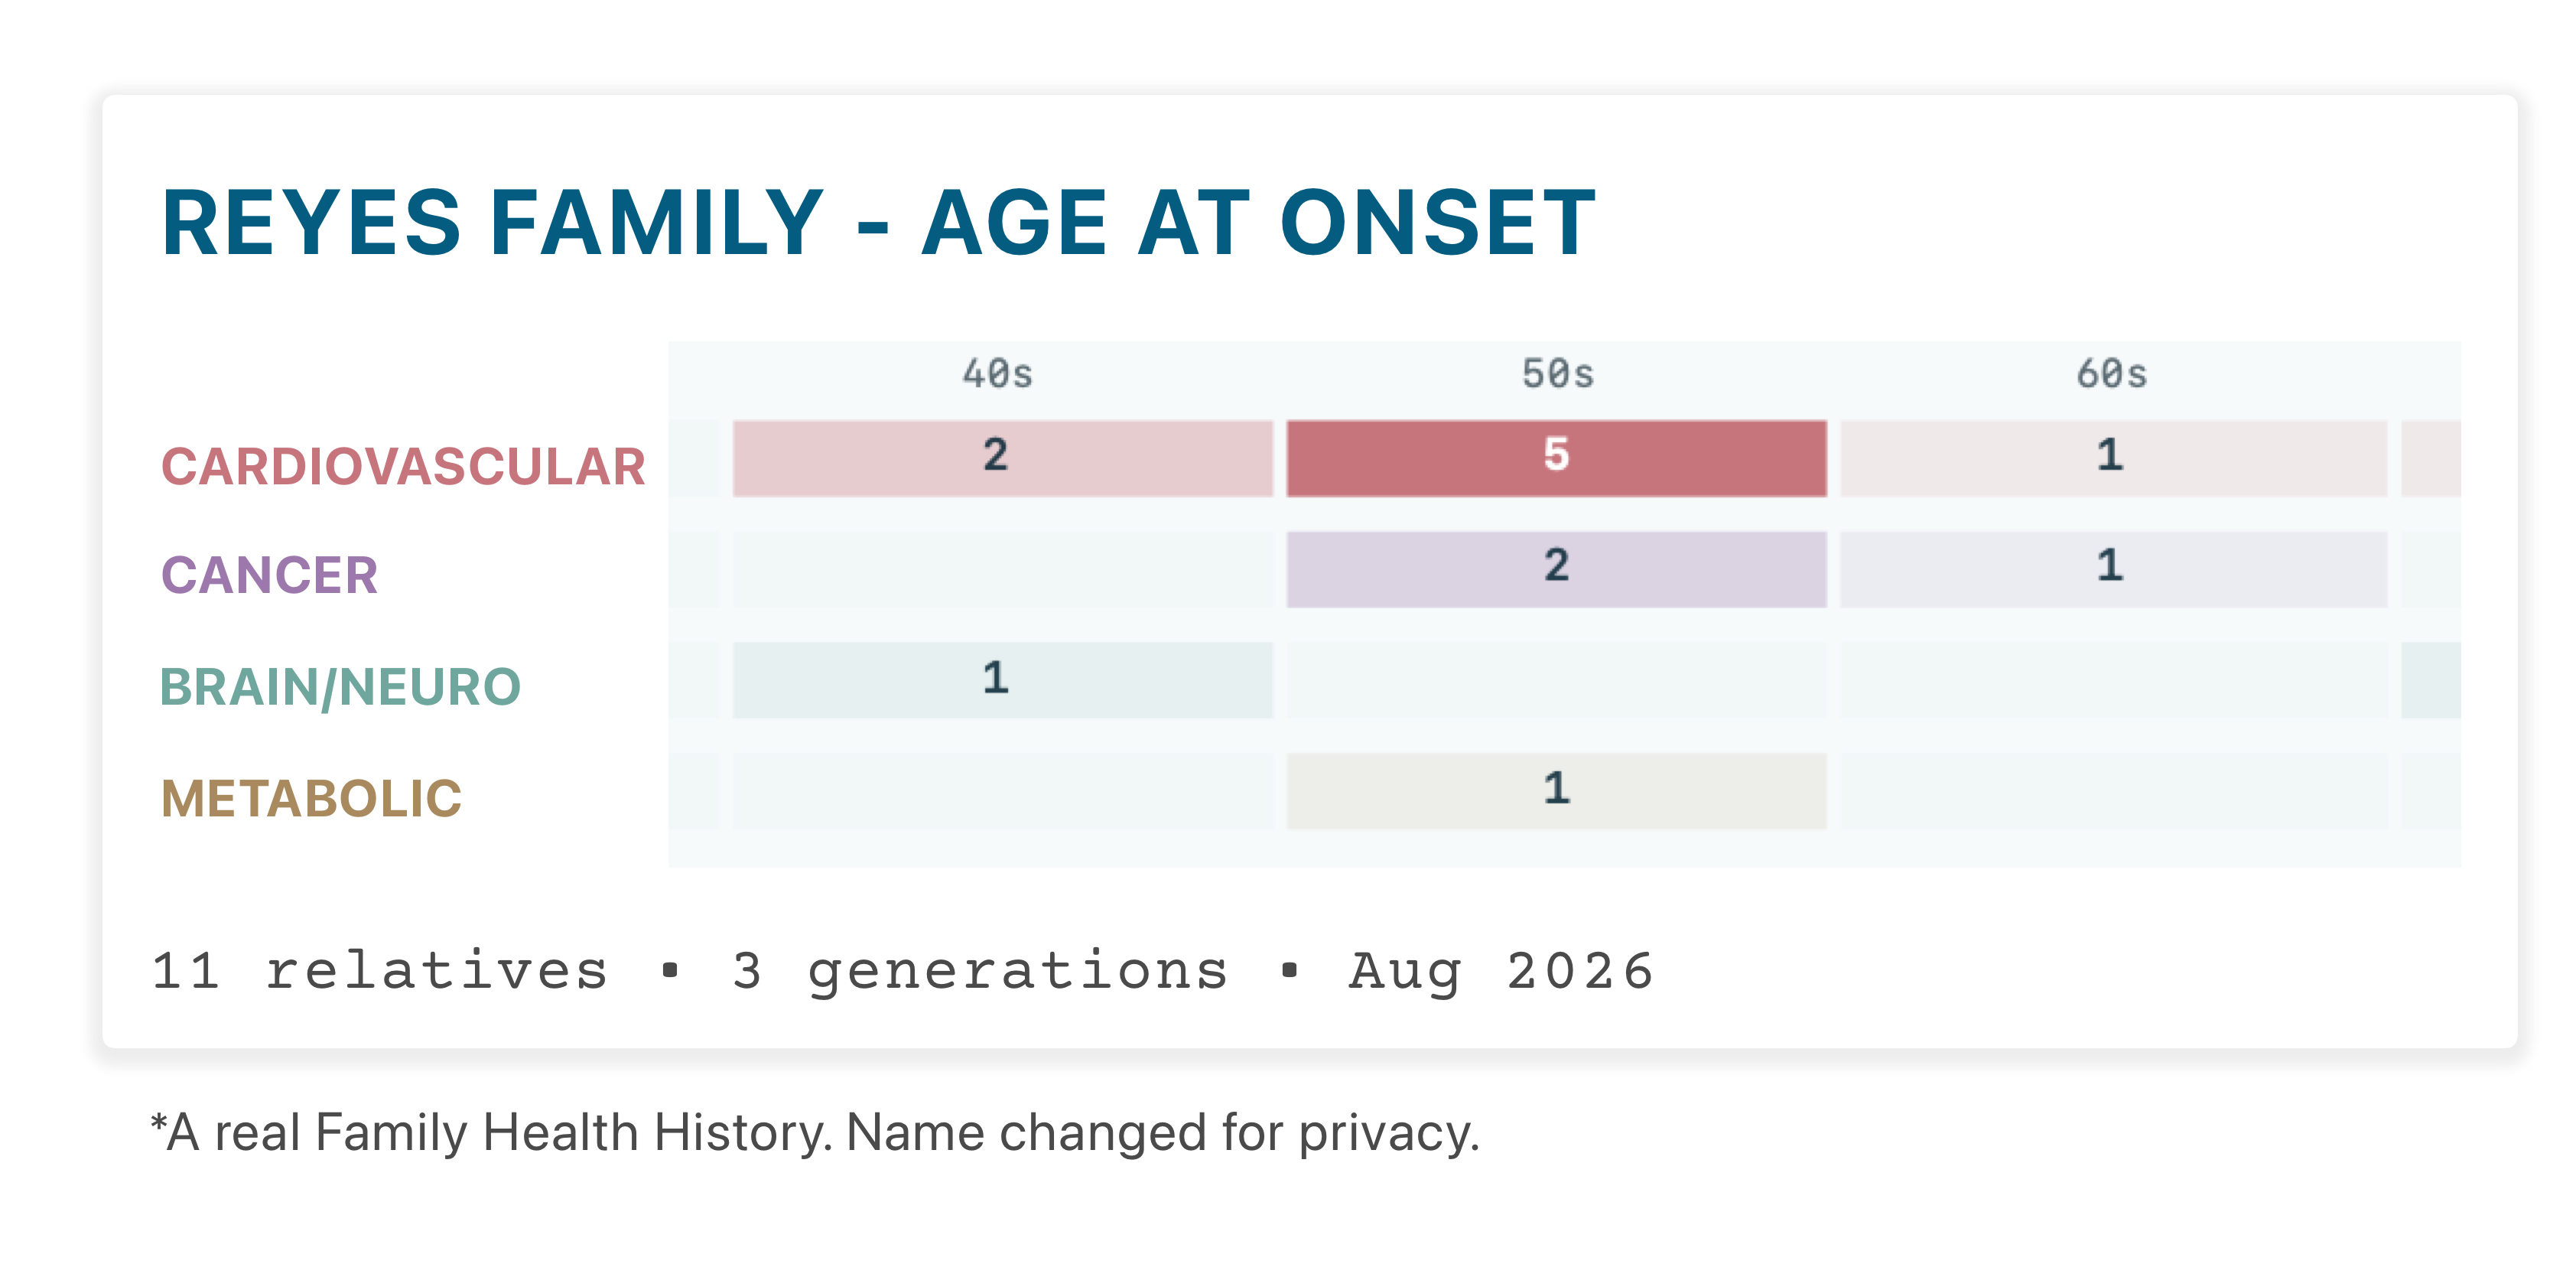
One part of the PDF is the Age at Onset heatmap below showing at a glance family history that might be concerning. This family had seven members with heart disease onset in their 50s or younger. Seeing this, your doctor could ask more questions and take more aggressive preventive measures than they might have had they not seen a chart like this.
There’s much more on how family health history works and how your information stays private at www.healthscout.co. In future posts, I’ll go deeper on the stories of Olivia Munn, Bob Harper, and William Nijjer, who each had heritable conditions and either took life-saving preventive measures because they knew about family health history or wish they’d had better information sooner.
HealthScout is an educational tool only and does not provide medical advice, diagnosis, or treatment. Always consult with qualified healthcare professionals for medical decisions.
HealthScout, including the Family Health History feature, is available now on the App Store. Using Family Health History is free for you and everyone you add.
I’m 88. I have high blood pressure and glaucoma but not diabetes. My mother had all three and lived past 100.
Recently, my PCP—by chance a cardiologist retired. He’s 77. He had bypass surgery a few years ago. I haven’t needed it. The “system” referred me to a new PVP-a young cardiologist. Eschewing a handshake or making eye contact or asking about FH, he looked at my numbers on his desktop said my cholesterol was “borderline” and recommended statins.
My former PCP practiced don’t take meds if you don’t have to. I do take a low dose med for my bp.
Deprioritizing” FH is one thing, ignoring is another. I’m now getting assembly-line medicine.
I told him I had my previous PCP as an emergency contact on my IPhone and asked whether I should replace it with his. He had no answer. I said “what if I do have a heart attack?” They’d take care of me at whatever hospital the ambulance would take me.
Everyone I know on statins complains of muscle and joint pains. I like going to the gym regularly. I told him that it was an important part of my quality of life that I didn’t want to give up.
He shrugged his shoulders and said “up to you” and referred me to a geriatrician. I was relieved. He probably thought “dementia”.
"Everyone I know on statins complains of muscle and joint pains." @Irwin everyone you know is old hahahaha.
I was worried about muscle pain too so started on a low dose. It didn't make my joint and muscle pains any worse even after I went on a higher dose.